Someone about to get a tattoo usually thinks about it for months. Where it will go, whether it will show when they are dressed, whether they will still feel the same about it in ten years. They will not go ahead with a design they are not entirely at peace with. There is one reason for that: they know it cannot be undone.
Aesthetic surgery does not always get the same care. And yet the decision here is both more permanent than a tattoo and incomparably more complex.
A tattoo is on the surface; surgery is underneath
Tattoo pigment sits in the second layer of the skin. Laser removal is possible but it is not easy: it takes several sessions spread over months, some colours never clear completely, and a difference in tone or a scar can be left behind. So even a tattoo is not truly reversible. It can only be reduced.
In surgery there is not even that much. Tissue that is removed is not put back. The fat cells taken out by liposuction leave that area permanently: the number of fat cells in an adult is largely fixed, and the body does not, in practice, restore the number removed from that region. What remains can still enlarge with weight gain, and fat can settle differently elsewhere, which is why the result depends on weight staying stable. Cartilage over-resected in a rhinoplasty does not grow back; if it has to be replaced, a graft must be taken from somewhere else. Skin that has been excised cannot be returned.
What is added is less simple than it looks, too. A breast implant can be removed, but what remains afterwards is the pocket the implant created, tissue thinned over time and skin that has stretched. "I will just have it taken out if I do not like it" does not mean a return to the state before it went in.
This is why the real question in aesthetic surgery is not whether you will like the result. The real question is: if you do not, what are you left with?
You describe the result; the surgeon chooses the route
A patient describes the result that bothers them: the stomach that sits over the waistband, the breast that has dropped, the nose that feels too big. Those descriptions are accurate and they are valuable. But naming the problem that produces that appearance is the surgeon's job, because the same appearance can come from different causes and each cause needs a different operation.
An earlier post in this series works through that gap with abdominal and breast examples. What matters here is this: whether an irreversible procedure is the right one depends less on the procedure itself than on the diagnosis that came before it.
What the decision actually rests on
The chain that determines the outcome of an aesthetic operation has three links, and the chain is only as strong as its weakest one.
- The right diagnosis. Naming the problem correctly. A wrong diagnosis means a wrong operation performed perfectly: technically there is no error, but the problem has not been solved and something has usually been added to it. This is the most frustrating situation in aesthetic surgery, precisely because there is no demonstrable mistake to point at.
- The right plan. There can be more than one route for the same diagnosis. Which one is chosen depends on the thickness and elasticity of your tissue, your age, your capacity to heal, the operations you have already had and what you expect. Part of the plan is also whether the work is done in one session or in stages.
- The right execution. However correct the plan, the operating theatre decides the result. Two operations carrying the same name do not produce the same outcome.
Most patients focus on the third link, because that is the visible one. The error that is hardest to reverse, however, is made at the first link.
What experience actually changes
Experience is not performing the same operation faster. What it buys is two concrete things.
The first is recognising the case that is not as simple as it looks. A patient may think of themselves as routine, when a previous operation, a history of weight change, a medication that affects healing, smoking, or an earlier procedure on the same area can change the plan from the outset. Some of these factors are not even on the patient's mind, because they never connected them to an aesthetic problem.
The second is knowing what to do when the plan has to change during the operation. Meeting a finding on the table that the examination did not predict is not rare. The decision taken in that moment is directly related to how many times something similar has been seen before.
Experience of this kind is shown by dates rather than announced by adjectives. Prof. Dr. Ferit Demirkan completed his plastic surgery residency at Gazi University between 1989 and 1997; he trained in microsurgery as a research fellow at the University of Utah in 1993-1994 and as a clinical fellow at Chang Gung University in Taiwan in 1997-1998; he became a Fellow of the European Board of Plastic Reconstructive and Aesthetic Surgery (FEBOPRAS) in 2004 and a professor in 2009. He still teaches: in 2025 he chaired the liposuction course at the 47th National Congress of the Turkish Society of Plastic, Reconstructive and Aesthetic Surgery and taught rhinoplasty at the 32nd European Course in Plastic Surgery in Zagreb. Those dates can be checked; the phrase "very experienced" cannot.
So there are questions that tell you more than "how many of these have you done":
- In this operation, what would make you change the plan on the table?
- What is the most common complication in this procedure, and what is done if it happens?
- What will this operation not fix?
The last question is the most valuable one.
The hospital is not a comfort choice
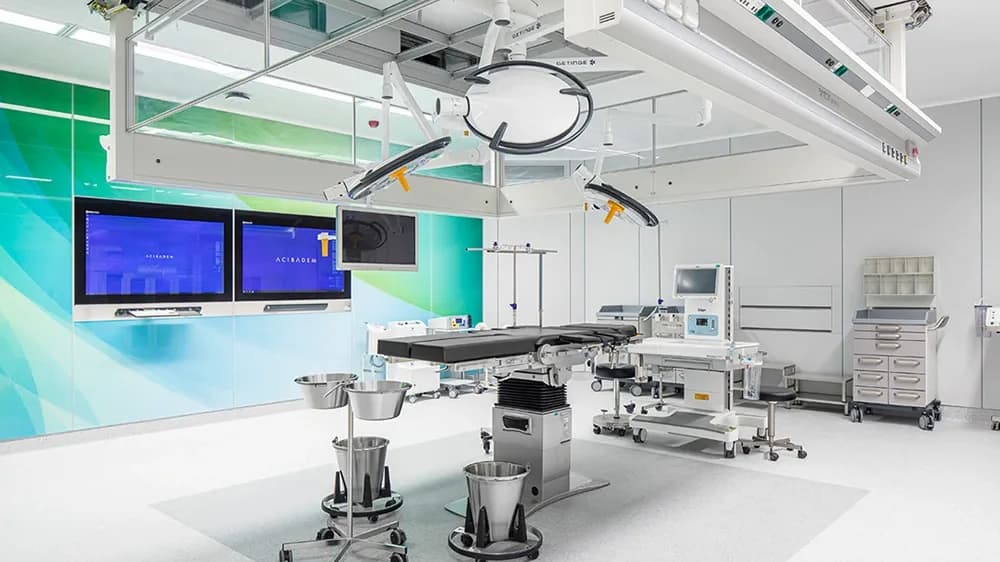
Where the operation takes place is a decision about safety, not about the aesthetics of the result. Operating in a full-service hospital means that the capacity to manage a complication, from intensive care to a blood bank, sits under the same roof. Aesthetic surgery is planned surgery and the odds of needing that capacity are low; but when it is needed there is no substitute for it.
Prof. Dr. Ferit Demirkan operates in the theatres of Acıbadem Ataşehir Hospital and Medicana Ataköy Hospital, both in Istanbul. Knowing where you will be operated on, who will give the anaesthetic and how many nights you will stay is your right, and you should know it before the day itself.
Why the gap between two prices is confusing
Two quotations for the same operation can differ considerably, and the difference usually comes not from bargaining but from a difference of scope, which an earlier post in this series sets out line by line.
For the purposes of this article there is only one thing to add: the price is paid once, the result is carried for years. A cheap quotation is usually cheap because something has been taken out of it, and what has been taken out is rarely the result itself. It is whatever was securing the result: the stay, the tests, the follow-up, and a written answer to what happens if there is a complication.
Turkish Ministry of Health regulations do not permit health-service prices to be published, which is why there are no figures here.
The first operation is your best chance
In aesthetic surgery a revision is almost always harder than the first operation. The reason is not a surgeon's reluctance but the tissue itself: after the first operation scar tissue forms in the area, the anatomical planes stick to one another, the blood supply changes and there is usually less tissue left to reshape.
The practical consequence is simple. The best moment to make the right decision is the moment before the first operation. After that, every correction is made in a narrower space.
Surgery does not replace looking after your body
The body that will carry the result is the same body that has to heal it. Smoking impairs the circulation of tissue and directly affects wound healing. Weight change after surgery alters the result over time, particularly in body contouring. Sun on a fresh scar can darken it permanently.
So "you only have one body" applies not only to the decision to operate but to the years that follow it. Surgery is a starting point. What preserves the result over the years is not surgery.
Ask yourself before you decide
- How long have I been thinking about this? Did I want the same thing a year ago?
- Am I doing this for myself, or under the influence of a person or a setting?
- Did the surgeon also tell me what will not improve?
- If the result is not what I expect, what is the next step, and has it been discussed?
- What is in the quotation and what is not? Are the follow-ups and the complication terms in writing?
- In ten years, will I still want to have made this decision?
Someone who will not get a tattoo without putting it through those questions should not make a far more permanent decision more quickly.